

There is a strange thing that happens when your pain is questioned often enough: eventually, you begin questioning it too. You wake up hurting, but instead of simply acknowledging the pain, you put it on trial.
Is it bad enough today? Am I struggling enough to call the doctor? Do I deserve relief, or should I wait until it becomes unbearable?
Somewhere along the way, I stopped asking what my body needed and started asking whether I had suffered enough to warrant being treated.
That last sentence is the kicker: Have I suffered enough to warrant going back to my doctor? To the emergency room?
Not am I in pain? I already know the answer to that. The question is whether I am in enough pain. Enough to make the phone call. Enough to ask someone to drive me. Enough to sit beneath the fluorescent lights of an emergency room and explain myself to a stranger who may already be wondering what I really came there for.
That is the calculation people with chronic pain are forced to make. We do not simply measure the pain. We measure the risk of asking for help.
I know that risk from experience.
A Ten on the Pain Scale
I remember one time when I went to the emergency room of a very busy hospital because I was having severe abdominal pain. It was the first time in my life that I understood what a real ten on the pain scale felt like.
The emergency room was packed, so I was left on a gurney in the hallway. I lay there curled into the fetal position, waiting for the pain to ease, but it was not getting any better. I was sweating and shaking. The pain was so horrific that I could barely breathe.
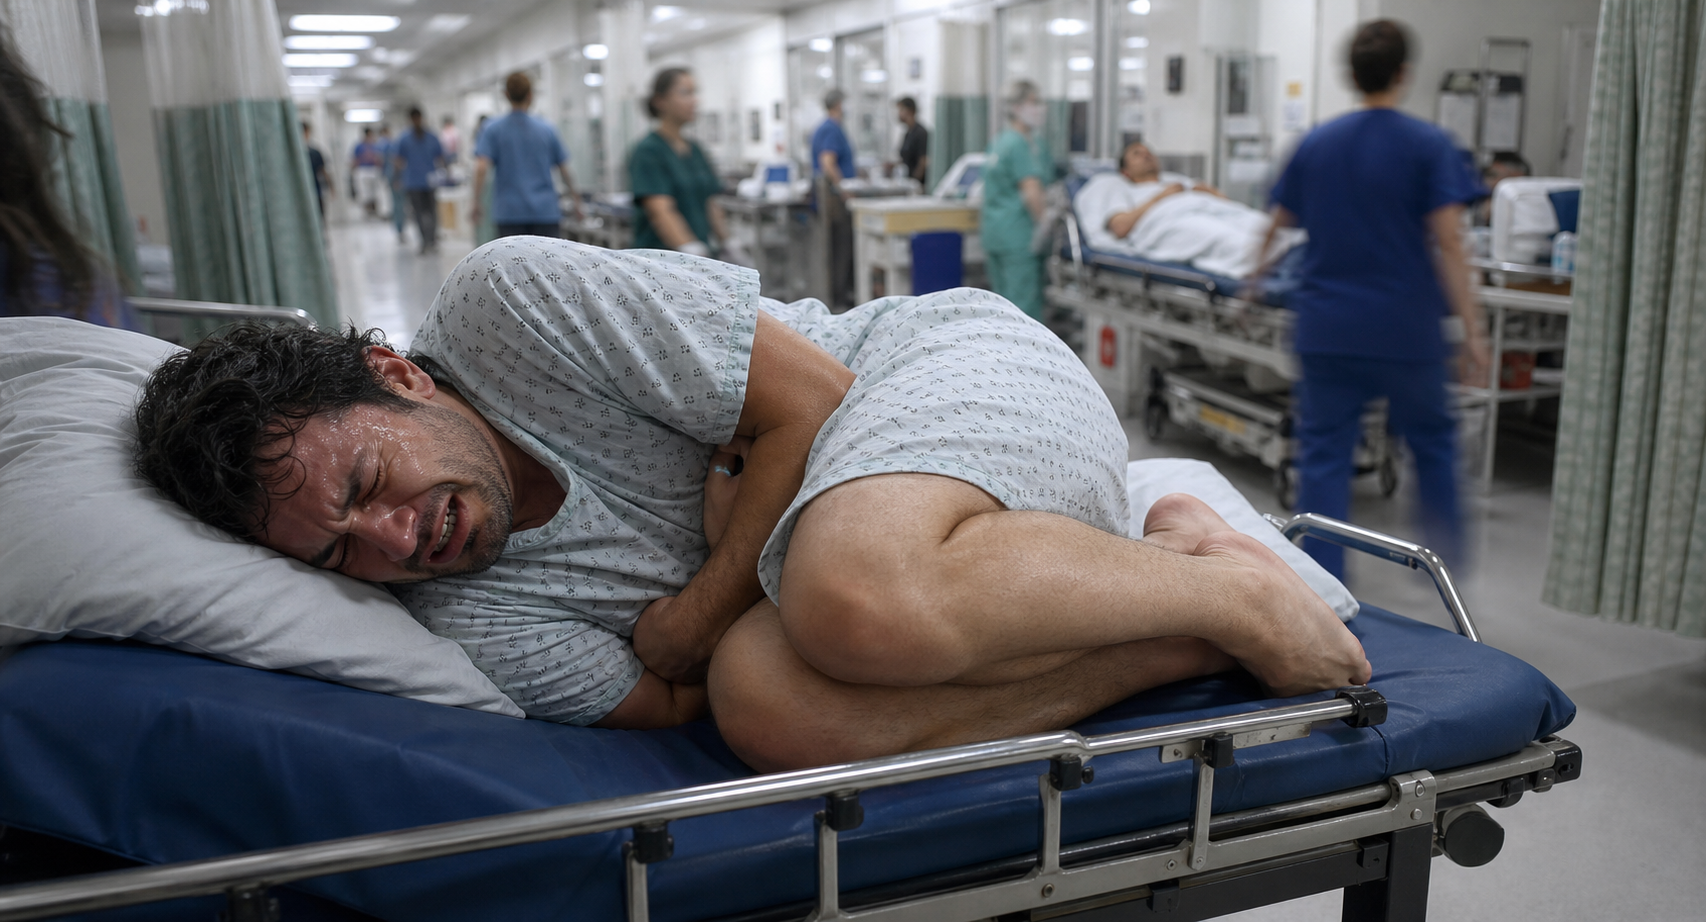
At the time, I thought something had torn in my stomach or abdomen because of my previous bariatric surgery. That turned out not to be the cause, but I did not know that while I was lying there. All I knew was that something felt terribly wrong inside my body.
Eventually, someone came and gave me a shot of morphine. It did not touch the pain. Then I was left in the hallway again, waiting for a room to open.
I remember calling for help. My face showed exactly how much agony I was in. I could barely catch my breath. Sweat was pouring down my face, and tears were coming from my eyes. There was no performance. There was no decision about how much pain to show. My body had taken over.
A nurse walked past me a couple of times while getting something from a nearby closet. At one point, she looked at me and said, “Maybe if you stopped grimacing, your pain would get better.”
Then she rolled her eyes and walked away, as if I were faking the whole thing.
Never in my life had I been so furious. I remember wishing that she could feel the pain I was feeling, even for one minute. Not because I wanted another person to suffer, but because I wanted her to understand what she had dismissed with one sentence and the roll of her eyes.
That experience taught me something I have never forgotten: Even when the pain is impossible to hide, even when you are curled into a ball, shaking, sweating, crying, and barely able to breathe, someone may still decide that what they are seeing is a performance.
So when I ask myself whether I am in enough pain to go back to the emergency room, I am not only thinking about the pain.
I am remembering what it felt like to beg for help and be treated as if I were acting.
So I Wait
What if the next doctor thinks I am exaggerating? What if they look at my chart and see my medication before they see me? What if they decide I am seeking drugs instead of seeking relief?

So I wait.
I tell myself the pain might settle down. I change positions. I stretch. I use heat, ice, traction, and every other tool I have collected over the years. I take the medication I have been prescribed and watch the clock, hoping the pain will lower its voice.
I try to distract myself. I write. I turn on the television. I write. I walk Pepper if I can. She needs it and deserves it. I do everything possible to avoid becoming a patient again.
And while I wait, another voice joins the pain.
Maybe it is not really that bad.
That voice did not begin inside me. It was taught to me, one doubtful look at a time. One carefully worded question. One pause after I described my symptoms. One appointment where I felt less like a person asking for help and more like a suspect giving testimony.
After enough of those moments, you begin doing their questioning for them. You become your own skeptical doctor, your own judge and jury. You cross-examine every sensation before allowing yourself to admit that you need help.
Can I still walk? Then maybe it is not bad enough.
Can I still speak in complete sentences? Then maybe it is not an emergency.
Did I laugh at something five minutes ago? Then maybe I cannot be suffering that much.
But chronic pain does not always look like a crisis. Sometimes it looks like a person sitting quietly in a waiting room. Sometimes it looks like a smile, a joke, or a calm conversation. Sometimes it looks like someone who has become so practiced at carrying pain that nobody notices how heavy it has become.
That ability to function is not proof that the pain is minor. It is proof that I have had far too much practice.
The Performance Follows Me Into the Psychiatrist’s Office
The interesting thing is that this is almost exactly what I question and go through when I see a psychiatrist.

If I laugh at a joke the doctor makes, am I not depressed enough for treatment? If I smile during the appointment, does that mean the panic attacks I have outside the doctor’s office are fake? If I am calm and able to explain myself, will the doctor assume I am doing better than I really am?
It all comes down to the same question: Do I need to perform in the psychiatrist’s office too?
The problem is that there does not seem to be a correct way to perform.
If I am calm, perhaps I am not suffering enough.
If I become emotional, perhaps I am exaggerating.
If I ask directly for relief, perhaps I am drug-seeking.
If I smile in the psychiatrist’s office, perhaps I am not depressed enough.
Whatever role I choose, there is always the possibility that I have chosen the wrong one.
Before an appointment, I sometimes find myself rehearsing. I organize my symptoms and go over the timeline. Then I start thinking about how I should present myself.
I remind myself not to minimize the pain, because minimizing it is what I naturally do. At the same time, I worry that if I describe it too strongly, the doctor will think I am exaggerating. I wonder whether I should make a joke to ease the tension, then worry that laughing will make me appear too comfortable.
By the time I enter the office, I am no longer simply a patient. I am an actor trying to anticipate the expectations of an audience I cannot read.
Afterward, I replay the performance.
Did I explain it clearly enough?
Did I look like I was hurting?
Did the doctor believe me?
I can leave with a treatment plan and still spend the drive home wondering whether I passed some test that no one admitted I was taking.
Sometimes the experience leaves me feeling so ashamed or defeated that I hesitate to ask for help the next time. That may be the most dangerous consequence of all. When people are made to feel guilty for seeking treatment, they begin delaying treatment. They wait longer. They endure more. They try to manage alone until they cannot manage anymore.
And even then, they may still wonder whether it is bad enough.
When “It’s All in Your Head” Becomes a Referral
I bring up psychiatry because many chronic pain patients are seeing both kinds of doctors.
Some are seeing a pain management doctor who dismisses their pain as being “all in their head” and sends them away with a referral to a psychiatrist. Other pain management doctors may genuinely believe that psychiatric care could help as one part of treating the whole person.

Those are not the same thing.
There is a difference between offering mental health care as support and using psychiatry as a convenient place to send someone whose physical pain you have decided not to believe.
I know that difference because mental health treatment was part of my life long before chronic pain entered it.
I began seeing a psychiatrist for treatment-resistant depression when I was about twenty years old. I am fifty-four now. My chronic pain did not begin until I was around forty-nine, when I was diagnosed with Paget’s disease of the bone.
The depression came first.
The chronic pain came decades later.
That timeline matters to me. My pain was not invented by depression, even though depression can affect how a person experiences and copes with pain. My history with mental illness does not erase my physical diagnosis. It does not make the pain less physical, less real, or less deserving of treatment.
Being referred to a psychiatrist should never be used as a polite way of saying, “We do not believe you.”
At the same time, I am not ashamed that I see a psychiatrist. I have spent most of my adult life fighting treatment-resistant depression. Psychiatric care has helped me survive things many people never saw.
Mental health care is not the enemy.
Dismissal is the enemy.
I can need psychiatric care and pain management at the same time. One does not disprove the need for the other.
My psychiatrist does not make my Paget’s disease disappear. My Paget’s disease does not make my depression less real. I am one person living with both. Treating my mental health is not an admission that my physical pain is imaginary, just as treating my physical pain does not mean my mental health is irrelevant.
I should not have to choose which part of me is allowed to be real.
In the pain management office, I wonder whether I look like I hurt enough.
In the psychiatrist’s office, I wonder whether I look depressed or anxious enough.
In both rooms, I am asking the same exhausting question:
Do I have to stop being myself before someone will believe that I need help?
A laugh does not mean I am not depressed.
A smile does not mean my panic attacks are fake.
A calm voice does not mean my pain is mild.
A good day does not erase the terrible ones.
People are complicated. We can laugh while grieving. We can smile while depressed. We can speak calmly while panicking inside. We can experience happiness while living with an illness that has not gone away.
A person should not have to remain visibly miserable every second of every day to prove that their suffering is real.
What I Need From a Doctor
I do not need every doctor to agree with every conclusion I reach about my health. I do not expect them to hand me whatever treatment I request without asking questions. I understand that doctors have responsibilities, medical standards, and difficult decisions to make.
But I do need them to begin with curiosity instead of suspicion.

Ask me what the pain prevents me from doing.
Ask me how long it takes to recover after an ordinary trip to the grocery store.
Ask whether I am sleeping.
Ask what I have already tried, what helped, and what failed.
Ask what my life looks like when the pain is at its worst, not only what I look like during the fifteen minutes I am sitting in front of you.
Do not decide how much I am suffering by how convincingly I suffer in your office.
The same is true in psychiatric care. Let me laugh at something funny without turning that moment into evidence against my depression. Let me say that I had a good day without assuming the illness is gone. Let me explain that I can appear calm during an appointment and still experience panic attacks when I leave.
Look at the whole person, the whole history, and the whole pattern.
Do not judge an entire illness by one brief performance.
The Appointment Should Not Be an Audition
I should be allowed to laugh at a doctor’s joke and still tell the truth about my depression.
I should be allowed to walk into a pain management office without limping and still be believed when I say that walking hurts.
I should be allowed to smile without having my panic attacks questioned. I should be allowed to speak calmly without having the severity of my pain reduced. I should be allowed to have a good hour, a good day, or even a good week without losing the right to treatment for an illness that will still be there when the good moment passes.
A doctor’s office should not be a stage.
An appointment should not be an audition.
Treatment should not be the prize awarded to the patient who gives the most convincing performance.
I have spent years learning how to live while hurting. If I have become good enough at the performance to make you forget that I am in pain, that does not mean the pain is gone.
It means I deserve a standing ovation.
Thanks for reading Fess UP! My Journal Out Loud! This post is public so feel free to share it.

Member discussion: